Updated 2026-10-11 · Originally published 2026-03-29
Hormonal changes can overlap with thyroid symptoms and can affect the interpretation of some laboratory measurements, but an estrogen change alone does not establish the cause of hypothyroidism. Discuss menstrual or menopausal history, pregnancy, contraception, medicines and the actual thyroid results with your medical clinician. Testing should answer a defined question rather than attribute every symptom to a broad hormonal imbalance.
Evidence note: The original educational article below is preserved. Added guidance distinguishes established diagnostic methods from hypotheses and test limitations; original claims are not proof that a diet, infection panel or supplement causes or reverses thyroid disease.
Okay I’m going to need you to pay attention here…….
- If you’re on birth control
- If you’re pregnant
- Or if you’re in menopause…….YOU’RE AT A MUCH HIGHER RISK FOR HYPOTHYROIDISM!
Check out these stats:
- If you’re on birth control, you’re 25% more likely to develop Hashimoto’s
- Women with a history of more than 4 pregnancies are twice as likely to develop subclinical hypothyroidism (means undiagnosable) compared to women who have never been pregnant.
- Women with a history of more than 4 pregnancies are 6 times more likely to develop overt hypothyroidism compared to women who have never been pregnant.
- Women with at least one pregnancy have a 10% increased likelihood for Hashimoto’s compared to women who have never been pregnant.
- In women with positive thyroid antibodies (TPOAbs) early in pregnancy, up to 50% may experience postpartum thyroiditis.
- Hashimoto’s thyroiditis frequently manifests or worsens during perimenopause and postmenopause, with 70% of hypothyroidism cases diagnosed in women over 50. Women are 5–20 times more likely to develop it than men, often triggered by declining estrogen during menopausal years.
BIRTH CONTROL
If you’re on hormonal birth control, you’re likely dealing with estrogen dominance as we speak.
Your B.C. actually creates estrogen dominance by introducing synthetic estrogen and suppressing natural progesterone production. These contraceptives keep estrogen levels high to prevent ovulation but when you do this, your body may develop a state of functional hypothyroidism through several interconnected pathways that block your thyroid's effectiveness at a cellular level.
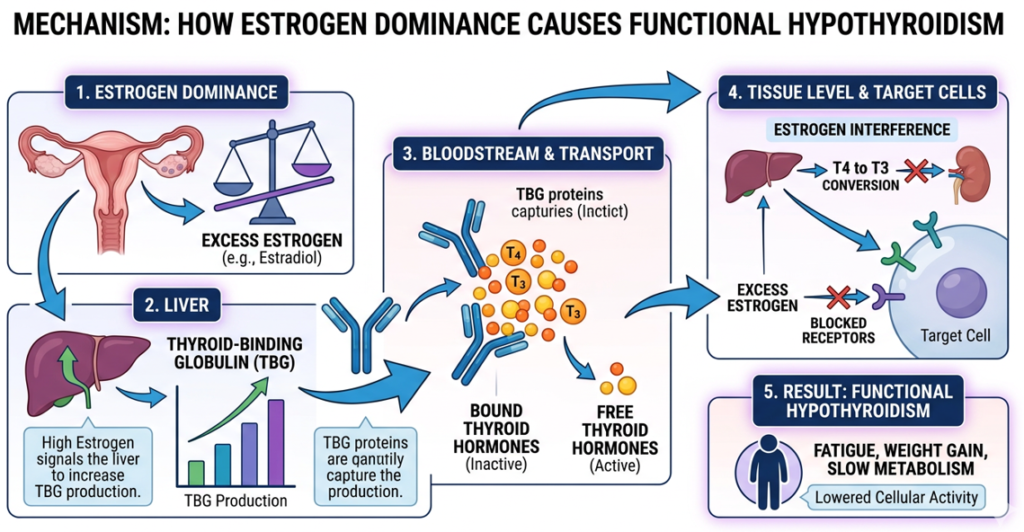
Primarily, the excess estrogen triggers your liver to overproduce thyroid-binding globulin (TBG), a transport protein that binds to your circulating thyroid hormones and renders them inactive. Even if your thyroid gland is producing a normal amount of hormone, this "binding up" means there is less free, active thyroid hormone available for your cells to use to regulate your metabolism. This can leave you with classic hypothyroid symptoms like weight gain, fatigue, and hair loss, despite having "normal" total hormone levels on standard lab tests.
DID YOU CATCH THAT?
Essentially, this problem can cause hypothyroid symptoms like weight gain, fatigue, and hair loss, and your Doctor will tell you you’re fine because their basic lab testing (which doesn’t test enough markers) says you have "normal" total hormone levels.
Wow! (This is how people like you end up on my site).
Anyways, high levels of estrogen can also interfere with the critical process of converting T4 (the storage hormone) into T3 (the active hormone), which primarily occurs in your liver and kidneys. By slowing this conversion, estrogen dominance effectively leaves your body with a deficit of the hormone it needs for energy and heat production. In some cases, estrogen can even block the uptake of thyroid hormones at the cell receptors or reduce the sensitivity of those receptors, making it harder for any available hormone to actually do its job. This creates a vicious cycle: as your thyroid function slows down, your liver becomes more sluggish at detoxifying and clearing excess estrogen, which only further exacerbates your state of estrogen dominance.
PREGNANCY
Pregnancy inherently causes a form of functional estrogen dominance. During pregnancy, estrogen levels rise dramatically—up to 6,000 pg/mL in the third trimester compared to a normal 30-400 pg/mL cycle—to support the placenta, fetal growth, and uterine expansion. While progesterone also rises to balance this, the massive increase in estrogen, sometimes paired with insufficient progesterone production, leads to symptoms of high estrogen, such as morning sickness, increased blood flow, and skin changes.
In the case of multiple pregnancies, this repeat offense to the body in the form of this severe estrogen dominance, causes hypothyroidism just like birth control did in the previous example. And you already read the stats above on pregnancy and its causal effect on hypothyroidism.
MENOPAUSE
As you enter menopause, the significant decline in your estrogen levels can disrupt the delicate balance of your endocrine system, potentially leading to an underactive thyroid.
Remember: your thyroid gland contains estrogen receptors!
So a loss of this hormone can directly cause a decline in thyroid function and even stimulate your pituitary gland to increase Thyroid Stimulating Hormone (TSH) levels. Furthermore, this hormonal shift often impairs your body’s ability to convert the inactive thyroid hormone (T4) into the active version (T3) your cells need to function.
Beyond these direct metabolic effects, the drop in estrogen may trigger increased systemic inflammation and a loss of immune regulation, raising your risk of developing autoimmune conditions like Hashimoto’s thyroiditis, which is a primary cause of hypothyroidism. Because the resulting symptoms—such as persistent fatigue, weight gain, and brain fog—mirror those of menopause itself, it is easy to mistake one for the other without comprehensive Hormone and Thyroid Testing.
And my guess is, your Doctor has done the basic lab testing and only that which insurance will pay for.
See, to reclaim your thyroid gland and your overall health, understanding all of these mechanisms and getting tested to see which of them are involved with your Hashimoto’s hypothyroidism, are critical.
- This requires comprehensive testing
- This requires an understanding of the testing and how to address these imbalances from a natural, diet & lifestyle perspective
- And finally, and this is important, this requires working with a Doctor who is not interested in masking the problem with a drug (levothyroxine, synthroid, armour thyroid, NP thyroid) because that’s what the insurance company says or what they’ll pay for.
Then for years, you might be on this medication that is “masking” the problem but not addressing the real cause(s).
And that’s where I come in.
I offer a free, 15-30 minute phone call consultation (a Discovery Call) to determine if you're a good fit for my office and to have any of your questions answered. From there we can discuss what tests you need (that your Doctor has ignored) and get some answers. Click here to take advantage of this offer - schedule that free call and start your journey to finally fixing your issue.
Don't suffer with thyroid problems / Hashimoto’s any longer. Let's find out what’s causing your hypothyroidism, and stop masking the problem - let's finally solve it!
Stress symptoms versus adrenal disease
Poor sleep and prolonged stress deserve attention, but adrenal insufficiency and other endocrine diseases require validated diagnostic pathways. Suspected adrenal insufficiency needs appropriate medical assessment; severe weakness, vomiting, fainting or dehydration should not wait for a wellness consultation.
Why collection context matters
Time of day, medicines, menstrual timing, pregnancy, contraception and menopause can affect hormone results. A single value detached from this context can be misleading. The clinician should explain why blood, urine or saliva sampling is appropriate for the question being asked and what the test cannot conclude.
Questions before ordering
Ask whether the result would change your care, whether confirmatory testing is needed and whether an endocrinologist or gynecologist should be involved. Testing offered by the practice is selected through consultation, not a promise that every person needs every hormone measured.
How is an underactive thyroid evaluated?
TSH is commonly the initial test, interpreted with free T4 when indicated. A raised TSH with low free T4 differs from a raised TSH with free T4 still in range. Pregnancy, pituitary disease, recent illness and medication use can change interpretation. Bring the actual reports, units and reference ranges rather than a recollection that a result was normal.
Does everyone need the same medication?
Levothyroxine is the usual hormone replacement for established hypothyroidism. The prescribing clinician determines whether treatment is indicated, the dose and follow-up. Persistent symptoms warrant a careful review, not unsupervised dose escalation. This practice resource is not an offer of prescribing or a substitute for medication monitoring.
What if symptoms persist?
A review can consider medication administration, supplements, sleep quality, anemia, mood, menopausal symptoms and other explanations. More tests are not automatically better. A useful test answers a specific question and has a realistic next step if the result is abnormal.
Questions and answers
What should I know about stress symptoms versus adrenal disease?
Poor sleep and prolonged stress deserve attention, but adrenal insufficiency and other endocrine diseases require validated diagnostic pathways. Suspected adrenal insufficiency needs appropriate medical assessment; severe weakness, vomiting, fainting or dehydration should not wait for a wellness consultation.
What should I know about why collection context matters?
Time of day, medicines, menstrual timing, pregnancy, contraception and menopause can affect hormone results. A single value detached from this context can be misleading. The clinician should explain why blood, urine or saliva sampling is appropriate for the question being asked and what the test cannot conclude.
Sources and further reading
- American Thyroid Association: Thyroid hormone treatment
- American Thyroid Association: Hashimoto’s thyroiditis
- NIDDK: Thyroid tests
- American Thyroid Association: Thyroid function tests
- NIDDK: Hashimoto’s disease
- NIDDK: Graves’ disease
- American Thyroid Association: Thyroid nodules
- Endocrine Society: Adrenal fatigue
- AAAAI: Limits of food IgG panel testing
- NIDDK: Diagnosis of celiac disease
- American Thyroid Association: Hypothyroidism during pregnancy
Educational information only, not medical advice, diagnosis or a treatment plan. Do not stop, start or change prescribed medication based on this resource. Pregnancy, children, significant heart symptoms and complex endocrine disease require appropriate medical care. Seek emergency help for chest pain, severe breathing difficulty, fainting, or high fever with confusion and a very fast heartbeat. A discovery call is not urgent medical care.